Learn the language of follow-up and Recovery and growth are different phases — Hair Transplant Terms Explained for First-Time Researchers
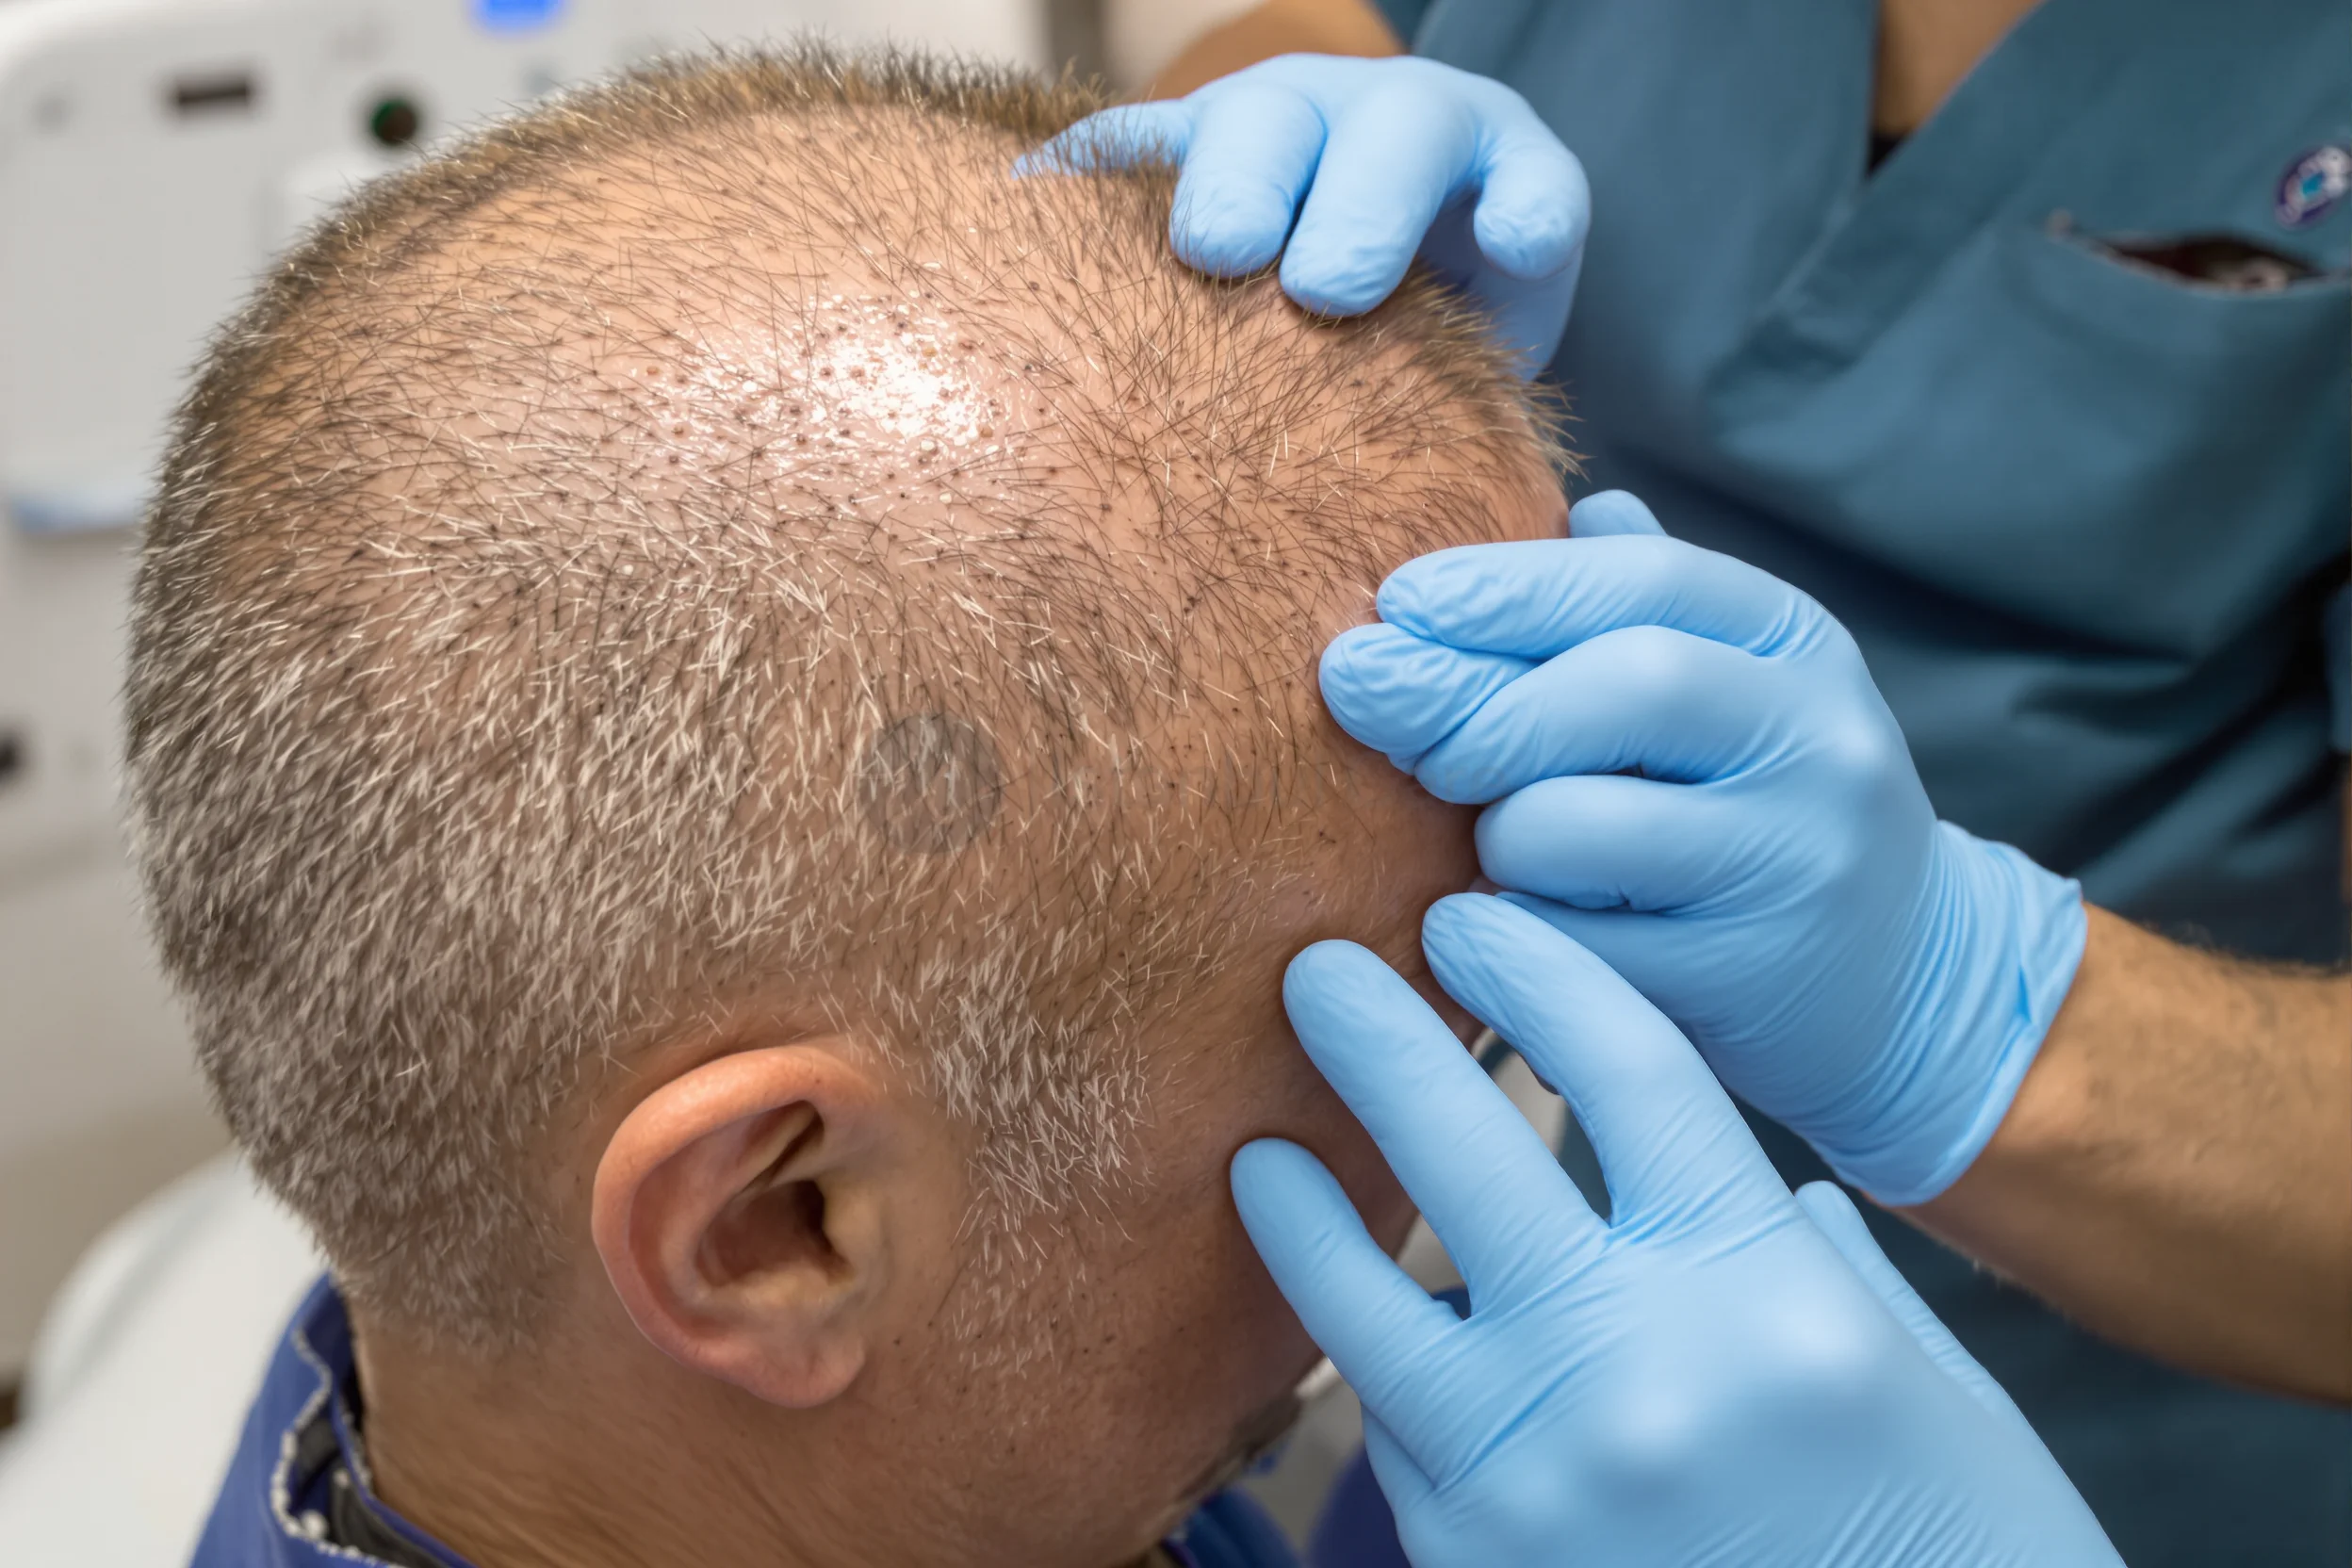
Research is easier when you can distinguish a medical term from a marketing phrase. A hair transplant moves follicles from a donor area to a recipient area; it does not create an unlimited new supply of hair. The donor area is usually discussed as the source of grafts, while the recipient area is where they are placed. Understanding those words helps you ask what can realistically be moved, which regions take priority, and what hair might continue to thin later.
Donor area and recipient area
The expression hair transplant turkey appears in searches for a destination, but geography does not define a surgical technique. Establish the actual provider, operating facility and clinician for your own date. A coordinator can explain travel arrangements; clinical diagnosis and consent require direct answers from an appropriately qualified professional.
FUE and FUT are approaches, not grades
In FUE, follicular units are typically taken individually from the donor area. FUT involves removing a strip of donor tissue from which grafts are prepared. Both approaches involve surgery and can leave scars, although the pattern of scarring differs. A provider may also use additional branded terms for tools or implantation methods. Ask exactly what the term describes, why that approach is proposed for you, who performs the steps, and what its limitations are. No label alone identifies a qualified team or guarantees a natural result.
Recovery and growth are different phases
Early healing after surgery is not the same as seeing a mature cosmetic result. Ask what changes are expected in the first days and weeks, when follow-up should occur, and what symptoms require medical attention. Individual timelines vary, so treat another patient's photographs as illustrations rather than a clock for your own recovery. Obtain aftercare instructions and a reliable clinical contact before leaving the treatment location. If travelling home soon after the procedure, establish how a local professional could obtain your operative details if needed.
Aftercare and follow-up
Aftercare can mean an early wash, medicines, written instructions, remote photographs or later clinical review. List which are included and who delivers them. If you need an examination after returning to the UK, ask how the overseas team would coordinate with a local clinician. Seek prompt local medical assessment for concerning symptoms rather than relying on a delayed message.
Bring the vocabulary back to decisions
If a provider promises an exact density, says every reader is suitable, or offers a graft count without discussing donor limitations, pause and seek clarification. If you cannot reconcile the website, consultation, and written agreement, wait before paying. You do not need to master surgical vocabulary to make a careful choice. You need enough understanding to recognize what is known, what remains provisional, and what only an individual clinical examination can resolve.
Learn the language of follow-up
An early postoperative check is different from judging the eventual appearance. Ask when the clinician wants photographs, what routine healing may look like, and when you should report a concern promptly. Clarify who can examine you if you have returned home. Keep a written explanation of any term you do not understand in the consent documents. If a provider cannot explain it without jargon, ask again before agreeing to treatment. Understanding the vocabulary should increase your ability to question the plan, not pressure you into accepting it.
Make a personal glossary
During calls, note unfamiliar words beside a plain-language explanation supplied by the clinician. For example, distinguish the area to be treated from the area supplying the grafts, and a preliminary estimate from a confirmed surgical plan. Ask what a term changes about decisions, recovery or cost. If an acronym is used to justify a premium fee, ask what the actual procedure would involve and who performs its steps. A brief glossary protects you from agreeing to language you recognize but do not understand. It also makes a later second opinion easier to discuss.
Use the vocabulary in your consultation
Bring a short list: diagnosis, donor assessment, recipient priorities, proposed graft estimate, technique, responsibilities, risks and follow-up. Ask the clinician to explain any unfamiliar term and to show where it appears in the written plan. If a coordinator uses one phrase and the clinical document uses another, check whether they refer to the same service. You should be able to describe what is planned without repeating advertising language. That understanding matters more than memorising every surgical abbreviation.